Emergency Dentist Care for Late-Night Dental Problems

A dental problem that flares up at 11:30 p.m. Rarely arrives politely. It tends to show up as a throbbing molar that keeps you pacing the hallway, a cracked front tooth after an evening fall, or swelling that seems to get worse by the hour. At that time of night, people are not looking for perfect timing or ideal convenience. They want pain relief, clear judgment, and a realistic answer to one question: does this need an emergency dentist now, or can it wait until morning?
That distinction matters more than most people realize. Some late-night dental issues are miserable but stable. Others can become serious quickly, especially when infection, uncontrolled bleeding, trauma, or airway concerns are involved. The hard part is that pain alone does not always tell the full story. A small cavity can hurt intensely, while a fractured tooth with nerve exposure may feel different from person to person. The role of an emergency dentist is not just to fix teeth after hours. It is to sort urgency from anxiety, reduce risk, and stabilize the situation until definitive treatment can be completed.
What counts as a real dental emergency at night
Not every dental problem needs immediate treatment, but several definitely do. In practice, the cases that deserve urgent attention usually involve one or more of four things: infection, trauma, bleeding, or severe pain that cannot be controlled with standard home measures.
A spreading dental infection is one of the biggest concerns. A tooth abscess may begin as tenderness or gum swelling, then progress into visible facial swelling, heat, pressure, a foul taste, or pain that seems to pulse with your heartbeat. If swelling starts to affect swallowing, speaking, or breathing, that moves beyond a routine dental complaint. It becomes urgent medical territory.
Trauma is another major category. Someone chips a tooth on a glass, gets hit during a late game, slips on wet stairs, or wakes to find a crown has come off around a heavily decayed tooth. Not every broken tooth requires a midnight visit, but a tooth that is loosened, pushed out of position, or completely knocked out often does. Timing makes a real difference, particularly for a permanent tooth that has been avulsed. The window for the best outcome is short.
Bleeding can also be deceptively important. Mild oozing after dental work is common, but bleeding that continues despite pressure, or bleeding after an injury that does not slow down, deserves prompt evaluation. People taking blood thinners may need extra caution here.
Then there is pain, the symptom that sends most people searching for an emergency dentist in the first place. A severe toothache at night tends to feel worse because the world gets quieter and there are fewer distractions. Lying down may increase pressure in the head and intensify throbbing. That does not automatically mean the situation is dangerous, but it does mean sleep is often impossible, and untreated pain can spiral into nausea, exhaustion, and poor decision-making.
The late-night problems dentists see most often
After-hours dental care follows patterns. Certain complaints come up repeatedly because they are the kinds of problems that become impossible to ignore when everything else is closed.
Severe toothache is near the top of the list. In many cases the cause is deep decay, an inflamed nerve, a cracked tooth, or infection around the root. Patients often describe the pain as sharp with cold, intense with sweets, or dull and constant until it becomes a pounding ache. Sometimes they have had mild sensitivity for months and assumed it would settle on its own. Then one night it tips over into something much harder to manage.
Lost fillings and crowns also show up frequently. On paper, they may sound minor. In reality, they can expose sensitive dentin, leave sharp edges, or uncover a tooth that is already badly weakened. A missing crown on a front tooth may be emotionally distressing. A missing crown on a back tooth may make chewing painful enough that the person stops eating solid food until it is addressed.
Broken teeth range from cosmetic chips to complex fractures. The difference is important. A tiny edge chip without pain can often wait for business hours. A large fracture with exposed pulp, bleeding from the tooth itself, or pain on air contact should not be brushed off. One of the more difficult cases is the vertical crack, which may not look dramatic but can cause intense bite pain and may extend below the gum line.
Wisdom tooth flare-ups also tend to worsen at night. When gum tissue around a partially erupted wisdom tooth becomes inflamed, food and bacteria can collect under the flap of tissue. The result can be swelling, foul taste, jaw stiffness, and significant discomfort. If the person also has fever or swelling that extends into the cheek, a same-night evaluation may be appropriate.
Children add their own category of urgency. A fall from a bed, a collision during sports, or a loose primary tooth after trauma can turn a quiet evening into a scramble. Pediatric dental emergencies need calm handling because the child’s distress often exceeds the visible injury. Parents may focus on blood in the mouth, which always looks like more than it is, while missing the more important signs such as a displaced tooth or lip laceration.
When to call an emergency dentist and when to go straight to the ER
This is where practical judgment matters. An emergency dentist is the right call for many urgent oral problems, but there are situations that belong in a hospital emergency department first.
Go to the ER if there is difficulty breathing, trouble swallowing, rapidly increasing facial swelling, significant trauma involving the jaw or head, uncontrolled bleeding, or signs of a serious infection such as high fever, confusion, or swelling that spreads into the eye area or neck. Those problems can move beyond dentistry.
Call an emergency dentist if the issue centers on a tooth, gum, crown, bridge, filling, or localized mouth injury and the person is stable overall. Many emergency dental offices can manage severe pain, drainage of abscesses, temporary restorations, trauma assessment, and urgent extractions. Some can also reposition or splint injured teeth, which can be crucial after an accident.
A useful rule from real-world triage is simple. If the main question is, "Can this tooth be saved or can this pain be stopped?" You likely need an emergency dentist. If the main question is, "Is this affecting breathing, swallowing, major bleeding, or broader medical safety?" The ER comes first.
What to do in the first hour at home
The first hour matters because good first steps can reduce pain, limit complications, and improve what the dentist can do once you arrive. Panic usually leads to the wrong moves, such as placing aspirin directly on the gum, trying to glue a tooth back with household adhesive, or taking random leftover antibiotics.
Use these measures instead:
- Rinse gently with warm salt water to clear debris and soothe irritated tissue.
- Apply a cold compress to the outside of the cheek for swelling or trauma, 10 to 15 minutes at a time.
- Take an over-the-counter pain reliever as directed on the label, if it is safe for you medically.
- If a permanent tooth has been knocked out, handle it by the crown, not the root, and keep it moist in milk or saliva while seeking urgent care.
- If bleeding is present, use clean gauze with firm pressure for 10 to 15 minutes without repeatedly checking.
Those steps are basic, but they are consistently useful. One common example is the knocked-out tooth. People often scrub it clean, wrap it in tissue, or let it dry on a countertop while deciding what to do. That sharply reduces the odds of successful reimplantation. Moisture and speed matter. Another example is a broken crown. https://dallaspdex148.terracolumn.com/posts/what-an-emergency-dentist-wants-you-to-do-after-a-tooth-injury Patients sometimes chew on the opposite side and hope for the best, only to arrive with a much larger fracture because the tooth beneath was already fragile. Temporary dental cement from a pharmacy can sometimes protect the area, but it should be used cautiously and never as a substitute for evaluation.
What happens during an emergency dental visit
A late-night visit is usually focused on stabilization, not on every final cosmetic or restorative detail. That is an important expectation to set. The goal is to control pain, stop active damage, reduce infection risk, and preserve as much tooth structure and function as possible.
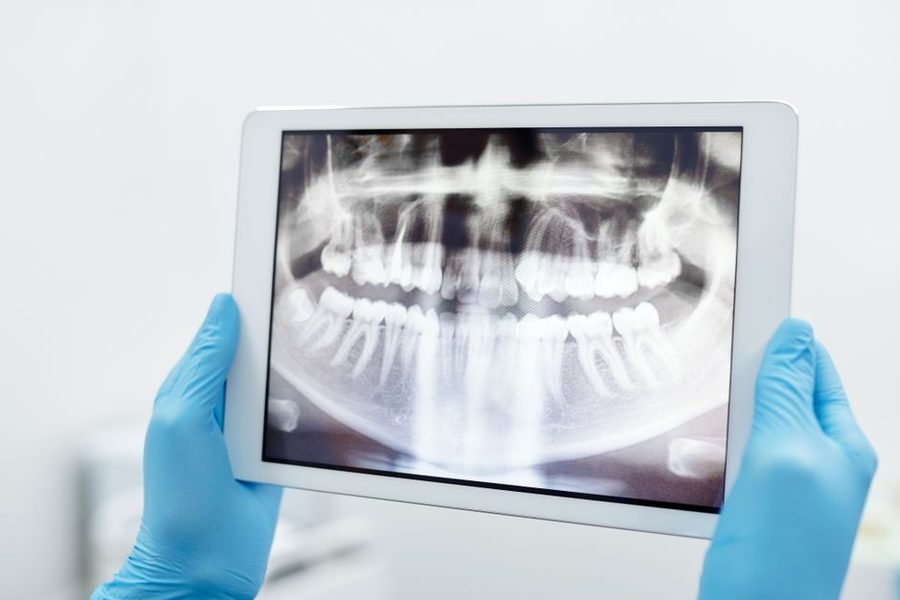
Assessment comes first. The dentist will ask when the pain or injury started, what triggered it, whether there was swelling, fever, sensitivity to temperature, or trauma, and what medications the patient has taken. X-rays are common because they reveal things that cannot be seen directly, such as root fractures, decay under old restorations, abscesses, or the position of a displaced tooth.
Treatment depends on the diagnosis. A painful infected tooth may need drainage, medication, and either root canal planning or extraction. A lost filling may be replaced temporarily or definitively if conditions allow. A dislodged tooth may be repositioned and splinted. A cracked tooth might receive a sedative dressing or temporary crown. If the pain comes from an inflamed nerve inside an otherwise restorable tooth, the dentist may perform emergency pulpal treatment to relieve pressure and buy time until full treatment can be done.
People are often surprised that antibiotics are not handed out for every toothache. That is good practice, not neglect. Antibiotics do not cure decay, fractures, or many forms of pulpal pain. They are useful when there is bacterial infection with swelling, drainage, or systemic signs, but they are not a substitute for removing the source of the problem.
The problems that can wait until morning, and the ones that should not
The line is not always neat, but some patterns are clear. A dull ache that responds to ibuprofen and does not involve swelling, fever, or trauma may be safe to monitor overnight. A small chipped tooth with no pain and no sharp edge can usually wait. Mild irritation from braces or a canker sore, though unpleasant, is generally not a true emergency.
By contrast, severe unrelenting pain, visible swelling, pus, a foul taste with pressure, facial asymmetry, a knocked-out adult tooth, or a tooth that suddenly becomes loose after trauma should not be left to chance. Neither should pain after a recent extraction if it is escalating sharply rather than improving, especially if there is bad breath or exposed bone suggestive of dry socket. Dry socket is not usually dangerous, but it can be excruciating, and timely treatment can make a dramatic difference.
One late-night pattern experienced dentists notice often is the patient who says, "It hurt for a week, but tonight it exploded." That wording usually reflects pressure building in or around the tooth. When symptoms change quickly, the threshold to seek urgent care should be lower.
The cost question, and why delaying can become more expensive
Emergency care raises practical concerns, especially cost. Fees vary by location, time of day, imaging needs, and the treatment required. A brief after-hours exam is not the same as an emergency extraction, reimplantation after trauma, or treatment involving sedation. Insurance may help with parts of the visit, but not every emergency office accepts every plan, and reimbursement details can be uneven.
Still, delay often carries its own price. A tooth that might have been saved with prompt treatment can become non-restorable after more fracture or infection. A minor abscess can spread. A crown that came loose may be recemented easily at first, but if the tooth sits exposed and breaks further, the solution can shift toward root canal treatment, a new crown, or extraction and replacement. From a purely financial standpoint, small problems have a habit of becoming large invoices when they are ignored.
There is also the less visible cost of lost sleep, missed work, poor nutrition, and unmanaged pain. A person with a severe molar infection may not sleep for two nights, then turn up dehydrated, exhausted, and still in pain. That kind of delay helps no one.
How to choose an emergency dentist when you are under pressure
Decision-making gets sloppy when someone is hurting. It helps to know what to look for before the next emergency happens, but even in the moment there are a few sensible filters.
Look for a practice that clearly states whether it offers true after-hours dental care or only next-day urgent slots. Those are not the same. Confirm whether the dentist can take diagnostic X-rays and manage trauma, infection, and extractions on site. Ask what forms of payment are accepted and whether they treat children if that applies. If the emergency involves a knocked-out tooth or facial injury, speed matters more than a perfect online review score.
A calm phone conversation often reveals a lot. Competent emergency dental teams tend to ask focused triage questions: How old is the patient? Is there swelling? Is there fever? Was there trauma? Is bleeding controlled? Those questions signal that they are sorting urgency rather than simply filling an appointment slot.
Preventing the midnight crisis no one wants
Many late-night dental emergencies are not fully preventable, especially accidents. But a surprising number begin as routine problems that were tolerated too long. Tiny cracks become larger. Loose fillings are ignored. Intermittent sensitivity gets explained away. A wisdom tooth that flares every few months is never evaluated. Preventive care is not glamorous, but it is the reason some people never need an emergency dentist at all.
A few habits make a measurable difference:
- Do not postpone treatment for recurring pain, sensitivity, or a loose restoration.
- Wear a mouthguard for contact sports and a nightguard if you grind heavily.
- Keep up with regular exams so small cracks, decay, and gum problems are caught early.
- Avoid using teeth to open packages or bite hard non-food items like ice.
- Save the phone number of a local emergency dentist before you need one.
That last point sounds mundane, but it is one of the most practical. People make better decisions at 2:00 p.m. Than at 2:00 a.m. Knowing where to call removes one layer of chaos.
Special situations that deserve extra caution
Pregnancy changes the picture slightly. Dental infections still need prompt attention, and severe pain should not simply be endured. The dentist may coordinate with the patient’s obstetric clinician, especially regarding medications and imaging, but emergency care remains appropriate when needed. Untreated infection is not safer just because the patient is pregnant.
Older adults may present differently as well. A person with dementia, diabetes, or multiple medications may not describe pain clearly. Sometimes the first sign is refusal to eat, facial touching, agitation, or swelling spotted by a caregiver. Denture-related injuries can also become urgent if they prevent eating or cause significant ulceration.
People who are immunocompromised need a lower threshold for evaluation. A dental infection that might remain localized in one person can progress more quickly in another. The same is true for those with a history of head and neck radiation, certain bone medications, or significant cardiac conditions where infection control matters more broadly.
What patients usually remember after the emergency is over
Once the pain has eased and the crisis passes, most people remember two things. First, they wish they had acted earlier. Second, they underestimate how much relief comes from simply having a clear plan. Even when a tooth cannot be saved that night, knowing what is happening and what comes next lowers the emotional temperature immediately.
Emergency dentistry is not just about rescue. It is about sorting the urgent from the non-urgent, preventing a bad night from becoming a dangerous one, and restoring enough comfort and stability for proper treatment to follow. Late-night dental problems have a way of making everything feel more alarming than it is, but they can also hide the problems that truly should not wait. When pain is severe, swelling is present, trauma has occurred, or bleeding will not stop, reaching an emergency dentist is not overreacting. It is good judgment.
Smyle Dental Bakersfield
2016 E St, Bakersfield, CA 93301, United States
+16614939040
FAQ About Emergency Dentist
What counts as a dental emergency?
Severe tooth pain, facial swelling, uncontrolled bleeding, a knocked-out or displaced tooth, and significant dental trauma may need prompt assessment. Trouble breathing or rapidly increasing swelling requires urgent medical help.
What should I do if a permanent tooth is knocked out?
Handle the tooth by the crown rather than the root, keep it moist, and contact a dentist immediately. Fast treatment can improve the chance of saving the tooth.
Can an emergency dentist treat severe tooth pain the same day?
Same-day care may be available depending on the cause and schedule. The dentist will examine the area, may take digital X-rays, and recommend treatment based on the diagnosis.
Should I go to the emergency room for dental swelling?
Seek urgent medical care for trouble breathing, difficulty swallowing, rapidly spreading facial swelling, or other severe symptoms. A dentist can assess the underlying dental cause and provide appropriate follow-up care.